


Pharma regulatory bodies like the FDA and EMA protect patients by enforcing pharma regulation that demands proven safety and efficacy. They review data, factories, and post-market reports. Yet regulatory capacity is uneven. WHO benchmarks national regulators against its Global Benchmarking Tool and publishes the list of authorities operating at maturity level 3 or 4, the levels that indicate a stable, well-functioning regulatory system.
Globally, harmonisation keeps growing. In December 2025, WHO reported that its network of WHO-Listed Authorities (WLAs) had reached 41 authorities from 39 countries, giving other regulators trusted reference points for reliance. Mutual recognition deals, such as FDA–EU inspection agreements, help agencies rely on each other’s work and speed access to quality medicines without lowering safeguards.
Table of Contents
What Are Pharma Regulatory Bodies?
Pharma regulatory bodies are official organizations that oversee medicines from lab to patient. Pharmaceutical regulatory agencies set rules for research, manufacturing, labeling, marketing, and post-market monitoring. They check if companies follow laws and keep drug information honest and complete.
Drug regulatory authorities protect public health by reducing risks from unsafe or poor-quality products. Moreover, they review clinical trial data and inspection findings before they approve new medicines. Therefore, they help people trust treatments and support fair access to essential therapies.
Core activities of these bodies include:
Review medicine safety, quality, and efficacy data
Inspect factories, labs, and distribution sites regularly
Enforce regulations and respond quickly to safety concerns
Educate healthcare professionals and the public about safe medicine use
Major Global Pharma Regulatory Bodies
Major pharma regulatory bodies protect medicine quality from lab to pharmacy. They set science-based rules, inspect sites, and review safety data. They also work with ministries, companies, and patients to keep benefits higher than risks.
These agencies share core tasks but work in different legal and cultural systems. They approve medicines, monitor side effects, react to new safety signals, and increasingly align guidelines to support global development.
Major examples include:
United States — FDA (Food and Drug Administration)
Europe — EMA (European Medicines Agency)
United Kingdom — MHRA
Japan — PMDA (Pharmaceuticals and Medical Devices Agency)
India — CDSCO
Canada — Health Canada
Australia — TGA
WHO — Prequalification Programme
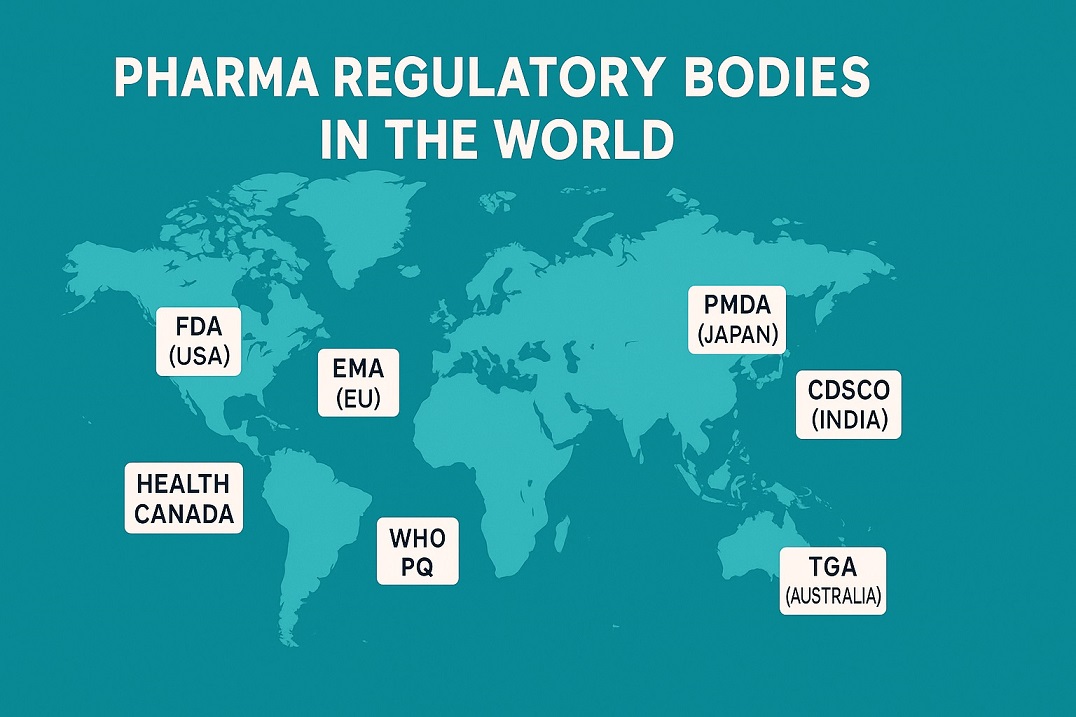
The FDA is America’s main drug and food watchdog. Moreover, it reviews safety, quality, and efficacy data before approving new medicines.
It shapes global standards, and many regulators follow its guidance closely.
EMA, the European Medicines Agency, helps Europe control medicine safety, quality, and efficacy. It coordinates expert reviews across countries.
Moreover, EMA supports faster access to important treatments.
It shares data and guidance with national regulators.
Centralised assessment of innovative and generic medicines.
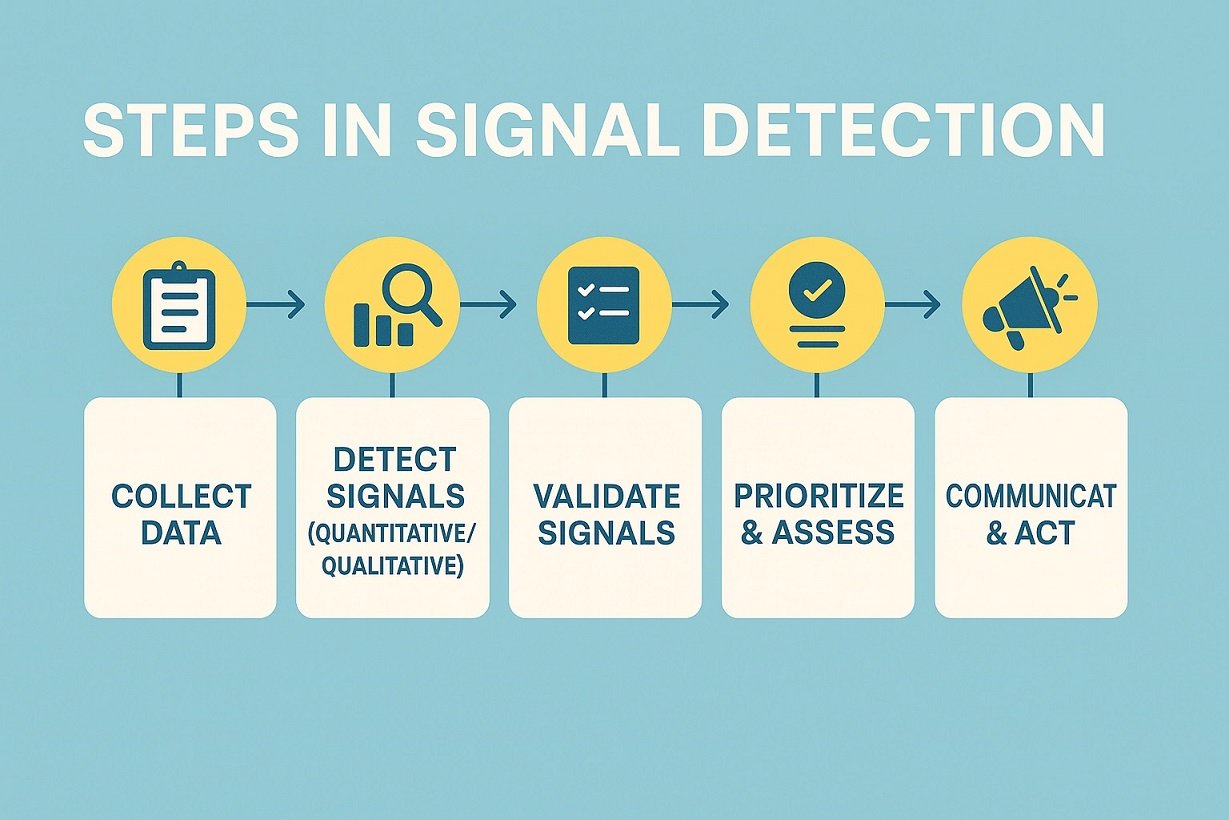
Continuous safety monitoring and signal detection.
Scientific advice on development and authorisation plans.
MHRA guides medicine and device safety in the United Kingdom and beyond. Moreover, it carefully reviews trial data and factory inspections before it accepts new products.
MHRA shares guidance globally, shaping standards for other regulators and healthcare teams.
PMDA oversees medicines and devices in Japan to protect public health. Moreover, it reviews data, inspections, and risks before it approves new products.
PMDA supports innovation while it keeps strict standards for safety and efficacy. It also works with global regulators to share findings and improve access for patients worldwide.
Scientific review of drugs and medical devices
Post-marketing safety monitoring and signal detection
Consultation on clinical trial and development plans
CDSCO regulates medicines and devices across India to protect public health. It sets standards for quality, safety, and lab testing.
Moreover, it reviews data, licenses factories, and controls imports. It works closely with global regulators.
Health Canada carefully regulates medicines and devices to protect people. It sets rules for quality, safety, labeling, and promotion.
Moreover, it reviews data before companies sell new medicines.
TGA oversees medicines and devices across Australia to protect public health. It sets strict rules for quality, safety, and manufacturing standards. Moreover, it reviews evidence before new treatments reach clinics and pharmacies.
The WHO Prequalification Programme checks key medicines, vaccines, and diagnostics. It helps countries without strong regulators find trusted, quality-assured products.
Moreover, it supports donors and agencies when they choose products for health programs.
Key Responsibilities of Regulatory Bodies
Regulatory bodies protect people from unsafe or ineffective medicines. They set rules for research, manufacturing, and marketing. Moreover, they guide companies so every step follows standards. Their work links science, ethics, and trust.
A key duty includes clinical trial oversight. Regulators review protocols, consent forms, and safety plans. They track trial progress and handle serious events quickly. Therefore, they confirm data quality before companies request approval. Regulatory submissions play a key role. Companies send structured dossiers with quality, safety, and efficacy data. Regulators assess benefits and risks, then decide if products enter markets. Strong processes support faster access without losing safeguards.
- Clinical trial oversight: regulators approve protocols and follow serious adverse events.
- Marketing authorisation: agencies assess quality, safety and efficacy data before approval.
- Post-market surveillance: agencies track side effects and act on new safety signals.
How Drug Approval Processes Differ Across Regions
Drug approval processes share goals but differ widely across regions. Each authority sets unique rules, timelines, and document formats. Moreover, local disease patterns and budgets shape their review priorities.
Some regulators accept global trial data, others request local confirmatory studies. Therefore, companies adapt strategies, sites, and submissions for every target market. These differences change launch speed, access, and development costs for patients worldwide.
Centralised regional review vs separate national approvals
Priority or fast-track routes vs standard review timelines
Acceptance of global trial data vs demand for local studies
How Regulators Work Together: Harmonisation, Inspections and Reliance
No regulator reviews every medicine and inspects every factory alone. Several international mechanisms let agencies share standards, inspection results and assessment decisions, which is why the same guideline can appear in FDA, EMA and MHRA expectations.
- ICH guidelines: Regulators and industry develop shared technical guidelines through ICH, and each region then implements them. For example, ICH Q9(R1) on quality risk management was adopted under ICH Step 4 on 18 January 2023, and the EMA version came into effect in the EU on 26 July 2023.
- PIC/S: The Pharmaceutical Inspection Co-operation Scheme brings GMP inspectorates together to develop and maintain harmonised GMP standards and quality systems for inspectorates, and to build mutual confidence between its participating authorities.
- Mutual recognition agreements: Under the amended US–EU Mutual Recognition Agreement, FDA and EU authorities can recognise each other’s GMP inspections of drug manufacturing facilities, reducing duplicate inspections. Both sides still reserve the right to inspect any site at any time.
- WHO-Listed Authorities (WLAs): WHO publicly lists regulators that meet its benchmarking and performance-evaluation requirements, so other countries can rely on their work.
- Reliance pathways: Some regulators formally take account of decisions already made by trusted agencies. Since 1 January 2024, the UK MHRA’s International Recognition Procedure has been open to applicants that already hold an authorisation for the same product from one of MHRA’s specified reference regulators.
For professionals, these mechanisms explain why an inspection outcome or an ICH guideline revision can affect work in several markets at once. When you prepare a dossier or an inspection, check which of these arrangements applies to the authority involved.
How WHO Rates National Regulators
WHO assesses national regulators with its Global Benchmarking Tool (GBT), which uses four maturity levels. Level 1 means only some elements of a regulatory system exist, and level 2 means an evolving system that partly performs key functions. Level 3, WHO’s minimum target, indicates a stable, well-functioning and integrated system, while level 4 reflects advanced performance with continuous improvement.
However, level 3 does not automatically bring WHO-Listed Authority status. It only opens the door to a further performance evaluation. As of December 2025, 41 authorities from 39 countries held WLA status for medical products.
In 2026, WHO extended the framework to medical devices with a transitional list of 12 authorities, current as of 1 July 2026, including FDA, MHRA, PMDA, ANVISA, NMPA and the European Medical Devices Regulatory Network. This status is temporary and was built from existing recognition lists rather than new evaluations.
Why Regulatory Knowledge Matters for Pharma Professionals
Regulatory knowledge keeps your daily work safe, legal, and efficient. You understand why rules exist, not just which SOP to follow. Therefore, you design processes that survive inspections and avoid costly mistakes. You prevent delays, failed batches, and compliance findings that hurt patients and your company.
This fluency also boosts your career in QA, RA, PV, and manufacturing. Managers trust people who speak the language of guidelines and dossiers. Moreover, you join key discussions earlier and influence decisions with clear, practical advice. You spot risks in documents and data before they grow. Continuous learning then keeps you ready for new rules and technologies.
Comparing FDA, EMA and MHRA Decision Pathways
FDA, EMA, and MHRA protect patients through similar regulatory goals. However, their systems do not work identically. Therefore, professionals should understand more than each agency’s name. They should know who reviews submissions, which pathway applies, and what happens after approval. This knowledge becomes especially valuable in Regulatory Affairs, QA, pharmacovigilance, and global submission roles.
Key points to compare include:
- Jurisdiction: United States, European Union, or United Kingdom
- Approval structure: National versus regional regulatory systems
- Submission pathway: Applicable dossier and marketing authorisation route
- Lifecycle oversight: Variations, inspections, safety monitoring, and compliance actions
Who Grants the Marketing Authorisation?
The comparison becomes clearer when you ask who takes the final legal decision. In the EU centralised procedure, EMA’s Committee for Medicinal Products for Human Use (CHMP) evaluates the application and issues a scientific opinion. The European Commission then takes a legally binding decision, and the authorisation is valid in all EU Member States as well as in Iceland, Liechtenstein and Norway.
In the United Kingdom, MHRA grants UK-wide marketing authorisations, either through its national routes or, since 2024, through the International Recognition Procedure. In the United States, FDA itself reviews and approves new drug and biologics applications. For a step-by-step view of how approval and compliance work at each agency, see our guide to drug regulatory agencies.
How to Build a Global Regulatory Strategy Across Major Markets
A global submission strategy should not simply copy one regulatory dossier into every market. Instead, teams should identify the responsible authority first. Next, they should compare regional evidence, submission, manufacturing, and pharmacovigilance requirements. Finally, they should identify gaps before submitting. This structured approach can reduce avoidable rework and improve regulatory planning.
The ICH Common Technical Document (CTD) makes this reuse possible. Under ICH M4, Module 1 holds region-specific documents, such as application forms and prescribing information, while Modules 2 to 5 (summaries, quality, nonclinical and clinical data) are intended to be common to all regions. In practice, teams can build one core technical dossier and prepare a separate Module 1 for each authority. Still, regional data expectations, such as requests for local studies, need a gap check before submission
Compare FDA, EMA, MHRA, and PMDA in One Guide
Final words
Regulatory bodies increasingly work through shared frameworks, including ICH guidelines, PIC/S cooperation on GMP inspections, mutual recognition agreements and WHO’s listing of trusted authorities. Together, these arrangements help agencies rely on each other’s work while each keeps its own legal responsibility.
As WHO extends this listing from medicines to medical devices, reliance on trusted agencies is likely to shape more approval and inspection decisions in the years ahead.
Your career grows when you understand these systems. Stay audit-ready and protect patients by committing to continuing education and structured regulatory learning.
FAQs
1️⃣ Does EMA approve medicines in the EU?
Not directly. In the centralised procedure, EMA’s CHMP evaluates the application and issues a scientific opinion. The European Commission then takes the legally binding decision, and the authorisation is valid in all EU Member States as well as Iceland, Liechtenstein and Norway.
2️⃣ What is a WHO-Listed Authority?
A WHO-Listed Authority (WLA) is a regulator that WHO has evaluated as meeting its benchmarking and performance requirements, so other regulators and procurers can rely on its work. As of December 2025, 41 authorities from 39 countries held WLA status for medical products.
3️⃣ Can the MHRA rely on FDA or EMA approvals?
Yes, through the International Recognition Procedure. Since 1 January 2024, applicants holding an approval for the same product from a reference regulator, such as FDA, EMA, Health Canada, PMDA, Swissmedic, TGA or HSA, can use this route. MHRA still makes its own decision on each application.
References
1- WHO – List of WHO-Listed Authorities (WLAs)
2-European Union (EU) Mutual Recognition Agreement
3 – FDA — U.S.–EU Mutual Recognition Agreement: Frequently Asked Questions and Answers (July 2023)
4 – MHRA — International Recognition Procedure (IRP)
5 – EMA — Obtaining an EU Marketing Authorisation, Step-by-Step
6 – WHO — List of National Regulatory Authorities Operating at Maturity Levels 3 (ML3) and 4 (ML4)
7 – Frontiers in Medicine — The World Health Organization Global Benchmarking Tool

Ershad Moradi, a Content Marketing Specialist at Zamann Pharma Support, brings 6 years of experience in the pharmaceutical industry. Specializing in pharmaceutical and medical technologies, Ershad is currently focused on expanding his knowledge in marketing and improving communication in the field. Outside of work, Ershad enjoys reading and attending industry related networks to stay up-to-date on the latest advancements. With a passion for continuous learning and growth, Ershad is always looking for new opportunities to enhance his skills and contribute to pharmaceutical industry. Connect with Ershad on Facebook for more information.

Protocol Deviations in Clinical Trials: Build an Audit-Ready Record
Protocol deviations can threaten participant protection and trial reliability. This practical guide explains risk-based classification, documentation, escalation, CAPA, and preventive oversight.

eCTD Publishing Software: The Right Features for Submission Success
Discover how eCTD publishing software organizes regulatory dossiers, validates electronic submissions, manages document lifecycles, and supports FDA and EMA workflows.

Pharmaceutical Analytical Testing Services: Essential Quality Insights
A practical guide to pharmaceutical analytical testing services: assay, impurities, dissolution, stability, microbial testing, validation and outsourced-laboratory oversight.